Wednesday, March 16, 2022

40Y/M C/O INVOLUNTARY MOVEMENTS OF B/L UL AND LL

CBBLE UDHC SIMILAR CASES

 THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HER /GUARDIAN'S SIGNED INFORMED CONSENT .HERE WE DISCUSS OUR INDIVIDUAL PATIENT'S PROBLEMS THROUGH SERIES OF INPUTS FROM AVAILABLE GLOBAL ONLINE COMMUNITY OF EXPERTS WITH AN AIM TO SOLVE THOSE CLINICAL PROBLEMS WITH COLLECTIVE CURRENT BEST EVIDENCE BASED INPUT 

Informant : Patients wife and son

 A 40Y/M who is a farmer by occupation was brought to the casualty with c/o involuntary movements of B/L upper limbs and lower limbs ,GTCS type ,not associated with uprolling of eye, tongue bite, involuntary micturition/defecation.

3 episodes in a day,and was taken to a local hospital and was treated conservatively.

No similar complaints in the past

No c/o headache ,head trauma, Loc, chest pain, palpitations


Past history:-N/k/c/o Dm/htn/epilepsy/ CAD/Ba/thyroid disorders.

H/o jaundice 1 month ago for which he went to local practitioner.


Personal history:-

Married

Occupation: Farmer

Diet - Mixed,

Appetite -Normal ,

Bowel Movement - Regular 

Bladder movements: Normal

No Known Drug Allergies

H/o alcohol consumption -Regularly 300ml since 20 yrs

H/o smoking since 20 years(3 packs/day)

No habit of other addictions


Family History: Not Significant


O/e:

Patient is conscious, coherent, cooperative 

No signs of Pallor, icterus, Cyanosis, Clubbing, Lymphadenopathy,Pedal Edema

Temp:98.5°F

Pr:99bpm

Rr:18cpm

Bp:110/80

Spo2: 99% at RA

GRBS: 24mg/dl --> 25%D--> 264mg/dl


SYSTEMIC EXAMINATION

Cvs: S1 S2 +, no murmurs

Rs: BAE +,NVBS heard

PA: soft,non tender 


CNS:-

Patient is conscious  

Speech is normal

No signs of meningeal irritation

Crania nerves- NAD 

Motor system: NAD

Sensory system: NAD

Gcs:- E6V2M6

                     - RIGHT                LEFT

PUPIL.       NSRL.                      NSRL

TONE UL NORMAL              NORMAL

             LL NORMAL             NORMAL

POWER UL NORMAL          NORMAL

               LL NORMAL          NORMAL                    

REFLEXES  

       a) BICEPS 2+                2+

       b) TRICEPS 2+              2+ 

       c) SUPINATOR 2+        2+

       d) KNEE 2+                   2+

       e) ANKLE 2+                 2+


Provisional diagnosis:- Alcohol withdrawal seizures


INVESTIGATIONS:-

HEMOGRAM

HB: 7.6

TLC: 7,700

N/L/E/M/B: 78/16/00/06/00

PCV: 22.8

MCV: 102.7

MCH: 34.2

MCHC:33.3

RBC: 2.22

PLT: 1.40

RBC: 2.22

PS: NC/NC With mild thrombocytopenia


RFT:

BLOOD UREA : 5.3 MG/DL

SERUM CREATININE: 2.7

SERUM ELECTROLYTES:

Na+ : 139

K+: 3.4

Cl-: 101

Ca: 8.1 


LFT

TB:0.56

DB: 0.17

SGOT:142

SGPT: 51

ALP: 190

TP: 4.7

ALBUMIN: 2.44

A/G: 1.08


SEROLOGY: NEGATIVE

RTPCR:- negative

FBS 122

HBA1C : 6.8%

ECG: 


CXR


2D ECHO: https://youtu.be/wFy9kCgDhVY

EF: 55%

TRIVIAL TR+ / AR + / NO MR

NO RWMA , NO AS/MS, SCLEROTIC AV

GOOD LV SYSTOLIC FUNCTION + 

NO DIASTOLIC DYSFUNCTION, NO PAH/PE

PLAN:-

1. 25% Dextrose IVF /IV/STAT

2. IVF 1 NS With 2 amp of thiamine/Iv/stat

3.IVF 5%Dextrose/Iv/Stat

4.IVF- NS, RL , DNS@ 100ML/HR

5.IVF 1 NS -2AMP of thiamine/IV/TID

6.Inj. pantop 40mg /iv/od

7. Inj.lorazepam 2cc/iv/SOS

8. Inform seizure activity

9.Monitor vitals hrly and grbs hrly


                            SOAP NOTES

DAY 1

AMC BED 3

S: no fever spikes  

 no fresh complaints

O:

O/e

Patient is c/c/c

Temp:Afebrile

Pr:86bpm

Rr:19cpm

Bp:140/90

Spo2:94% at RA

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender, Bs +

GRBS: 117mg/dl

A: ? Hypoglycaemic Seizures  

(Whipples triad:

+ Symptoms of hypoglycemia

+ Resolution of symptoms after glucose

+ Low plasma glucose level )

P: 

1.IVF- NS, RL , DNS@ 75ML/HR

2. IVF 1 NS With 2 amp of thiamine/Iv/tid

3.Inj. pantop 40mg /iv/od

4.Inj. zofer 4mg /iv/sos

5.Tab. Librium 5mg/po/bd

6. Inform seizure activity

7.Monitor vitals hrly and grbs charting hrly

Plan for USG abdomen and psychiatry referral I/v/o alcohol dependence

CRP:  NEGATIVE

ESR: 15MM


WARD UPDATE 

DAY 2

S: no fever spikes  

 C/o pedal edema since yesterday night( pitting type)


O:

O/e

Patient is c/c/c

Temp:Afebrile

Pr:92bpm

Rr:17cpm

Bp:110/80

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender, Bs +

GRBS: 152mg/dl


A: Hypoglycaemic seizures


P: 

1.IVF- NS, RL , DNS@ 75ML/HR

2. IVF 1 NS With 2 amp of thiamine/Iv/tid

3.Inj. pantop 40mg /iv/od

4.Inj. zofer 4mg /iv/sos

5.Tab. Librium 25mg/po/bd

6. Inform seizure activity

7.Monitor vitals hrly and grbs charting 4th hrly

8.2 egg whites /day

9.2 tbsp of protein in 1 glass of water/milk /po/tid


Plan for usg abdomen i/v/o pain abdomen

Plan to discharge

Advice at discharge 
1.Plenty of water
2.T.pan 40mg Po/OD/BF X 5D
3.T.MVT PO/OD X 2 WEEKS

45Y/F WITH C/O GENERALISED WEAKNESS SINCE 2 DAYS

 CBBLE UDHC SIMILAR CASES

THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HER /GUARDIAN'S SIGNED INFORMED CONSENT .HERE WE DISCUSS OUR INDIVIDUAL PATIENT'S PROBLEMS THROUGH SERIES OF INPUTS FROM AVAILABLE GLOBAL ONLINE COMMUNITY OF EXPERTS WITH AN AIM TO SOLVE THOSE CLINICAL PROBLEMS WITH COLLECTIVE CURRENT BEST EVIDENCE BASED INPUT 


45 years old P3L3 female, agricultural labourer by occupation, came to the casuality with C/O generalised weakness since 2 days.

H/O vomitings and loose stools 2 days back.


HOPI:

Patient was apparently asymptomatic 1 year back and then had H/O Neck pain and backache - dragging type of pain, not associated with any numbness, tingling sensation of upper and lower limbs.

Patient started taking NSAID daily once for pain for 1 month, then she visited orthopaedician and advised her to get MRI: L-Spine and after that she was advised for surgery.

Patient had difficulty in passing stools (constipation) since 1 month for which the patient went to the nearby doctor 2 days back.

She was put on Syp. Lactulose and after 1 day, the patient had 5 episodes of watery stools for 1 day, 2 episodes of vomitings for 1 day which subsided now.

Generalised weakness present since 2 days.


PAST HISTORY:

Not a K/C/O DM/HTN/BA/TB/Epilepsy/Thyroid disorders/CAD/CVA


Patient underwent ECSL for Right Renal stones (ECSL) 6 years back, Hysterectomy 20 yrs back and Left Cataract Surgery 6 yrs back.


PERSONAL HISTORY:

Diet- mixed

Appetite- Normal

Sleep- Adequate

Bowel and bladder movements- Regular

No known allergies

No addictions


Family history: not significant


GENERAL EXAMINATION:

Patient is Conscious, coherent, cooperative.

No Pallor, icterus, cyanosis, clubbing, koilonychia, lymphadenopathy, edema.


Vitals:

Temp.- Afebrile

BP- 110/70 mmHg

PR- 100 bpm

RR- 12 cpm

SpO2- 98%

GRBS- 138 mg/dL


SYSTEMIC EXAMINATION:

CVS- S1 S2 heard, no murmurs

RS- BAE+ NVBS+

P/A- Soft, Non-tender


CNS- 

Patient is Lethargic

GCS- 15/15

Sensory and motor systems - Intact

Cranial nerves- intact

Reflexes- Intact


INVESTIGATIONS


USG ABDOMEN:


CHEST X-RAY PA VIEW:


X-RAY L-SPINE:


X-RAY L-SPINE Report :


C-Reactive protein: Positive on DOA:5 (2.4 mg/dL)

RFT on DAY 6


PROVISIONAL DIAGNOSIS:

AKI on CKD secondary to ?anagesic neuropathy

Pyrexia under evaluation


TREATMENT GIVEN:

1. IV Fluids NS and RL @ UO+50 ml/h

2. Inj. Optineuron 1 amp in 100 ml NS

3. Inj. PANTOP 40 mg IV OD

4. Inj. Lasix 20 mg IV BD (if sBP>110 mmHg)

5. Inj. Neomol 100 ml IV SOS (if temp>101 F)

6. Tab. PCM 500 mg PO SOS

7. GRBS - 6th hrly

8. I/O Charting

9. Monitor vitals 4th hrly


Orthopedics referral:


Nephrology Referral:


SOAP NOTES:


Day 2 

S: 

Generalised weakness present

No fresh complaints


O:

Temp.- Afebrile

BP- 120/70 mmHg

PR- 98 bpm

RR- 18 cpm

SpO2- 97% at RA

GRBS- 103 mg/dL


A:

Viral Pyrexia with Thrombocytopenia

AKI secondary to ?Sepsis


P:

1. IVF - NS,RL,DNS @ UO+100 ml/h

2. Inj. PANTOP 40 mg IV OD

3. Inj. Zofer 4 mg IV SOS

4. Inj. Lasix 40 mg IV BD (if sBP>110 mmHg)

5. Inj. Neomol 100 ml IV SOS (if temp>101 F)

6. Tab. PCM 500 mg PO/SOS

7. Tab. Doxycycline 100 mg PO/BD

8. Monitor vitals 4th hrly

9. I/O and Temp. Charting


Day 3

S:

C/o burning micturition, nausea (+), decreased appetite, 

No h/o fever, vomitings


O:

Pt is C/C/C

Temp- afebrile

Bp- 120/70 mmhg

PR- 74bpm

RR- 16cpm

SPO2- 99% 

CVS- S1 S2 heard

Rs- BAE+

CNS- NFND

P/A- Soft, Non-tender


A:

Viral pyrexia with thrombocytopenia

AKI secondary to ?GE 

With UTI secondary with R renal calculi


P:

1. IVF- NS RL DNS UO+ 50ml/hr

2. Inj. Optineuron 1amp in 100ml NS IV/OD

3. Inj. Pantop 40mg IV OD

4. Inj. Zofer 4mg IV OD

5. Inj. Neomol 1amp in 100ml NS IV if temp >101F

6. T. PCM 500mg PO/SOS

7. Temperature and I/O charting

8. Vitals monitoring


Day 4 

S:

C/o burning micturition, nausea (+) decreased appetite, 

No h/o fever, vomitings


O:

Pt is C/C/C

Temp- afebrile

Bp- 110/70 mmhg

PR- 72 bpm

RR- 17 cpm

SPO2- 98% 

CVS- S1 S2 heard

RS- BAE+

CNS- NFND

P/A- Soft, Non-tender


A:

Viral pyrexia with thrombocytopenia

AKI secondary to ?GE 

With UTI secondary with R renal calculi


P:

1. IVF- NS RL DNS UO+ 50ml/hr

2. Inj. Optineuron 1amp in 100ml NS IV/OD

3. Inj. Pantop 40mg IV OD

4. Inj. Zofer 4mg IV OD

5. Inj. Neomol 1amp in 100ml NS IV if temp >101F

6. T. PCM 500mg PO/SOS

7. Temperature and I/O charting

8. Vitals monitoring


Day 5 

S:

C/O decreased appetite and nausea+

No fever spikes


O:

Pt is C/C/C

Temp- Afebrile

Bp- 110/80 mmhg

PR- 82 bpm

RR- 18 cpm

SPO2- 99% 

CVS- S1 S2 heard

RS - BAE+

CNS- NFND

P/A- Soft, Non-tender


A:

Viral pyrexia with thrombocytopenia

AKI secondary to ?GE 

With UTI secondary with R renal calculi


P:

1. IVF- NS RL DNS UO+ 50ml/hr

2. Inj. Optineuron 1amp in 100ml NS IV/OD

3. Inj. Pantop 40mg IV OD

4. Inj. Zofer 4mg IV OD

5. Inj. Neomol 1amp in 100ml NS IV if temp >101F

6. Inj. Lasix 40 mg IV BD if sBP>110 mmHg

7. T. PCM 500mg PO/SOS

8. T. Doxycycline 100 mg PO/BD

9. Syp. Lactulose 15 ml PO/HS

10. Syp. Aristroxyme 15 ml PO/TID

11. Syp.Cremaffin 5ml PO/TID HS

12. Temperature and I/O charting

13. Vitals monitoring

14. GRBS monitoring 12 th hrly


Thursday, March 3, 2022

59Y/F with hyponatremia

CBBLE UDHC SIMILAR CASES

THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HER /GUARDIAN'S SIGNED INFORMED CONSENT .HERE WE DISCUSS OUR INDIVIDUAL PATIENT'S PROBLEMS THROUGH SERIES OF INPUTS FROM AVAILABLE GLOBAL ONLINE COMMUNITY OF EXPERTS WITH AN AIM TO SOLVE THOSE CLINICAL PROBLEMS WITH COLLECTIVE CURRENT BEST EVIDENCE BASED INPUT

A 59Y/F  brought to the casualty with c/o involuntary movements of B/L upper limbs and lower limbs ,GTCS type , with uprolling of eye, tongue bite, involuntary micturition, lasting for 2.min , with post ictal confusion + ,aura -.

H/o vomitings, (4-5 episodes in a day), nonbilious, non projectile, food particle as content

H/o pain abdomen since yesterday diffuse type, 

No c/o cold, cough, fever, burning micturition, headache ,trauma, Loc.


Past history:-N/k/c/o Dm/htn/epilepsy/ CAD/Ba/thyroid disorders.


Personal history:-

Married

Occupation Housewife

Diet  - Mixed,

Appetite -Normal ,

Bowel Movement - Regular 

Bladder movements: Normal

No habit of  addictions

No Known Drug Allergies

Menopause attained


Family History: Not Significant


O/e:

Patient has altered sensorium 

No signs of Pallor, icterus, Cyanosis, Clubbing, Lymphadenopathy,Pedal Edema


Vitals;-

Temp:98m5

Pr:89bpm

Rr:17cpm

Bp:140/80

Spo2:97% at RA

GRBS: 160mg/dl

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender

Cns:-

Patient is conscious but drowsy 

Speech  is incoherent

No signs of meningeal irritation

Cranial nerves- NAD 

Motor system: NAD

Sensory system: NAD

Gcs:- E4V2M6

                           -         RIGHT               LEFT

PUPIL.                    NSRL.               NSRL

TONE         UL        NORMAL       NORMAL

                     LL        NORMAL       NORMAL

POWER    UL         NORMAL       NORMAL

                    LL         NORMAL       NORMAL                    

REFLEXES  

       a) BICEPS               2+                    2+

       b) TRICEPS            2+                    2+ 

       c) SUPINATOR       2+                    2+

       d) KNEE                   2+                    -

       e) ANKLE                 2+                    2+

       f) PLANTAR        extensor          extensor

Investigations:- 

ABG

PH  7.44

PCO2 24.0

PO2 107

HCO3 16.1

ST HCO3 20.0

HEMOGRAM: 

HB: 13.5

TLC: 16,800

N/L/E/M/B: 86/09/01/05/00

PCV: 38.1

MCV: 80.8

MCH: 28.6

RBC:4.72

RDW-CV :12.6

RDW-SD: 41.7

PS: NC/NC

PLT:-1.1

CUE-

Alb :+

Sugars:nil

Pc:4-5/Hpf 

RBS 164mg/dl

SERUM ELECTROLYTES


Blood Urea : 16 MG/DL

Serum Creatinine: 0.7

Serum calcium:10.9

Serum phosphate: 2.4

LFT

TB: 1.35

DB: 0.3

SGOT:19

SGOT:25

ALP: 163

TP:7.6

ALBUMIN:4.9

A/G: 1.87

SER.LIPID PROFILE: 

Total cholesterol:171mg/dl

Triglycerides: 153mg/dl

HDL: 48

LDL:98

VLDL:30

TFT(3/3/22):

T3:0.71

T4;9.10

TSH:4.91

SPOT URINE SODIUM 122

SPOT URINE POTASSIUM 21.0

URINARY CHLORIDE 15

SERUM FOR OSMOLALITY 269

RTPCR: NEGATIVE

SEROLOGY: NEGATIVE

ECG: 


CXR


2D ECHO:   https://youtu.be/vwqwpJczZvg

TRIVIAL TR+ / AR+ / NO MR

GOOD LV SYSTOLIC FUNCTION + 

NO RWMA , NO AS/MS , SCLEROTIC AV

DIASTOLIC DYSFUNCTION +, NO PAH /PE


USG ABDOMEN:- IMP

Right simple renal cortical cyst

CT BRAIN IMP-No abnormality detected in brain


Diagnosis :- Seizures secondary to hyponatremia


Plan:-

1)Inj. levipril 1 gm in 100ml Ns iv stat

2)inj. pan 40mg iv stat

3)3% Nacl infusion @ 10ml/hr followed by 4th hrly serum electrolytes

4)0.9 % Ns @ 75ml/hr

5)Strict I/O charting

6)Monitor vitals hrly


                                SOAP NOTES

DAY 1:

Amc Bed 8

Day 1

59yr/F


S: 2 fever spikes  


O:

O/e

Patient is c/c/non cooperative

Temp:Afebrile

Pr:89bpm

Rr:17cpm

Bp:120/70

Spo2:97% at RA

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender

CNS: E4V5M6

Pupils : B/l Nsrl

                     RIGHT               LEFT

PUPIL.          NSRL.                NSRL

TONE UL NORMAL        NORMAL

              LL NORMAL        NORMAL

POWER UL NORMAL     NORMAL

                 LL NORMAL     NORMAL                    

REFLEXES  

       a) BICEPS 2+               2+

       b) TRICEPS 2+            2+ 

       c) SUPINATOR 2+       2+

       d) KNEE         -.            -

       e) ANKLE     2+             2+

       f) PLANTAR extensor extensor


Didn't pass stools

GRBS: 100mg/dl


A: Seizures secondary to chronic hyponatremia (hypovolemia- resolved) 


P:

1.Ivf - 3%  Nacl @ 15ml/hr to be I/D A/to sr.electrolytes 4th hrly   

2.inj monocef 1gm/iv/bd

3.inj pan 40mg/iv/od

4.inj zofer 4mg/iv/sos

5.inj neomol 100ml /iv/ if temp > 101.1°F

6.Monitor vitals 2nd hrly

7.Head end elevation upto 30°


6PM:- 

3%Nacl stopped

0.9% Nacl @ 50ml/hr


DAY 2 


Amc Bed 8

Day 2

59yr/F


S: no fever spikes  

 no fresh complaints


O:

O/e

Patient is c/c/c

Temp:Afebrile

Pr:89bpm

Rr:17cpm

Bp:140/90

Spo2:97% at RA

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender

Didn't pass stools

GRBS: 114mg/dl


A: Seizures secondary to chronic hyponatremia (hypovolemia- resolved) 


P:

1.Ivf - 1 Ns with 1 amp of optineuron /iv/od

2.inj monocef 1gm/iv/bd

3.inj pan 40mg/iv/od

4.inj zofer 4mg/iv/sos

5.inj neomol 100ml /iv/ if temp > 101.1°F

6. Syp cremaffin 10ml.tid

7.Monitor vitals 2nd hrly


Ward update

Day 3

59yr/F


S: no fever spikes  

 no fresh complaints

no pain abdomen

O:

O/e

Patient is c/c/c

Temp:Afebrile

Pr:80bpm

Rr:19cpm

Bp:130/70

Spo2:99% at RA

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender

Didn't pass stools

GRBS: 151mg/dl


A: Seizures secondary to hyponatremia (hypovolemia- resolved) 


P:

1. Plenty of oral fluids

2.T.pcm 500mg/po/od

3.T.pan 40mg/po/od

4.syp.mucaine gel /po/bd

5. Syp cremaffin plus po/hs

6.Monitor vitals 4th hrly

Ward update

Day 4

59yr/F


S: no fever spikes  

 no fresh complaints

no pain abdomen

O:

O/e

Patient is c/c/c

Temp:Afebrile

Pr:86bpm

Rr:17cpm

Bp:120/70

Spo2:98% at RA

Cvs: S1 S2 +, no murmurs

Rs: BAE +

PA: soft,non tender

GRBS: 136mg/dl


A: Seizures secondary to hyponatremia (hypovolemia- resolved) 


P:

1. Plenty of oral fluids

2.T.pcm 500mg/po/od

3.T.pan 40mg/po/od

4.syp.mucaine gel /po/bd

5. Syp cremaffin plus po/hs

6.Monitor vitals 4th hrly

Wednesday, February 16, 2022

90Y MALE WITH RIGHT SIDED DEVIATION OF MOUTH

CBBLE UDHC SIMILAR CASES

THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HER /GUARDIAN'S SIGNED INFORMED CONSENT .HERE WE DISCUSS OUR INDIVIDUAL PATIENT'S PROBLEMS THROUGH SERIES OF INPUTS FROM AVAILABLE GLOBAL ONLINE COMMUNITY OF EXPERTS WITH AN AIM TO SOLVE THOSE CLINICAL PROBLEMS WITH COLLECTIVE CURRENT BEST EVIDENCE BASED INPUT 


Patient was brought to casualty with complaints of deviation of mouth to right since yesterday morning,c/o slurring of speech since yesterday


HOPI: 

A 90Y/M who was a farmer by occupation (staying at home since 10-15Y) Patient was apparently asymptomatic 1 yr back. Patient c/o nocturia (10-12x) overnight and went to local hospital and diagnosed with DM-2  and since then he is on regular medication .Since yesterday patient woke  up from sleep. Patient complaints of deviation of mouth to right side and slurring of speech since yesterday.


Outside BP :190/100mmhg

No c/o involuntary micturition/defecation

No c/o involuntary movements

No c/o dysphagia 

No c/o UL/LL weakness noted

No c/o fever,cold,cough

No c/o  burning micturition since 1 month

No c/o sob, orthopnea


PAST HISTORY

k/c/o diabetes since 1 year and on regular medication since then

Not a k/c/o HTN/CAD/TB/BA 

No past surgical history 


PERSONAL HISTORY:

Married

Previously farmer

Appetite: Normal

BowelsBladder movements: Regular

 Addictions: 

Alcohol consumption (Occasional -90ml)

Had habit of smoking but stopped 5yrs ago

No other addictions


FAMILY HISTORY: Not significant


O/E :

Pt is c/c/c ,well oriented to time,place, person.

Pallor +


No signs of icterus, clubbing, cyanosis, lymphadenopathy, pedal edema.


Vitals: 

Temp: Afebrile

Pr: 62bpm

Rr:17cpm

Bp:160/90 mmhg

Spo2: 97% on ra

Grbs:129mg%


Systemic Examination:

Cvs:S1S2 heard, no murmurs heard

Rs: BAE+ ,NVBS heard

P/A: Soft, nontender


CNS:- 

pt conscious with Slurred speech

No signs of meningeal irritation 

                                        RIGHT               LEFT


1) TONE         UL        NORMAL       NORMAL

                         LL        NORMAL       NORMAL


2) POWER    UL          5/5                  5/5

                        LL           5/5                  5/5


3) HANDGRIP              100%


4) REFLEXES  

       a) BICEPS               +                    +

       b) TRICEPS            +                    + 

       c) SUPINATOR      +                    +

       d) KNEE                   +                    +

       e) ANKLE                -                     -

       f) PLANTAR        Mute             Mute


5) CEREBRAL SIGNS:

Finger nose coordination: +

Knee heel in coordination: +

Sensory system:- unable to examine


Investigations:-

HEMOGRAM

HB: 10.9

TLC: 4200

N/L/E/M/B:74/18/2/6/00 

PCV: 31.5

MCV: 95.3

MCH: 33.1

MCHC:34.7

RBC:3.31

PLT:1.74

RDW-CV :15.8

RDW-SD: 57.2

PS: NC/NC

BGT:- B POSITIVE


RFT:

BLOOD UREA :  30MG/DL

SERUM CREATININE: 1.1

URIC ACID:4.4

SERUM ELECTROLYTES:

Na+ : 139

K+: 2.7

Cl-: 99


LFT

TB: 1.19

DB: 0.28

SGOT:34

SGOT:10

ALP: 124

TP:5.8

ALBUMIN:3.81

A/G: 1.91


SEROLOGY: NEGATIVE

HBA1C : 6.8

FBS:141

PLBS: 94

CXR:-


ECG:-


2D ECHO:-https://youtu.be/XwX7t-Engh0

Imp:-

-Trivial TR+ ; no MR/AR

-No RWMA/No MS/AS ; sclerotic AV

-Good LV systolic function

-Diastolic dysfunction + ; No PAH/PE


MRI brain (16/2/22):-

Imp:-

-Acute Lacunar infarct in right corona radiata

-Old Lacunar infarcts in left thalamus and left corona radiata

-Chronic small vessel ischaemic changes


Carotid Doppler:(17/2/22):-


Provisional diagnosis:-

Acute ischemic CVA with UMN type of left facial palsy with acute infarct in right insular cortex.

Plan:-

1)Tab.clopotab 75mg po od

2)Tab.Ecospirin 75mg po od

3)Tab.atorvad 20mg po od

4)Inj.optineurin 1amp in 100ml Ns iv/od

-MRI Brain


Wednesday, February 9, 2022

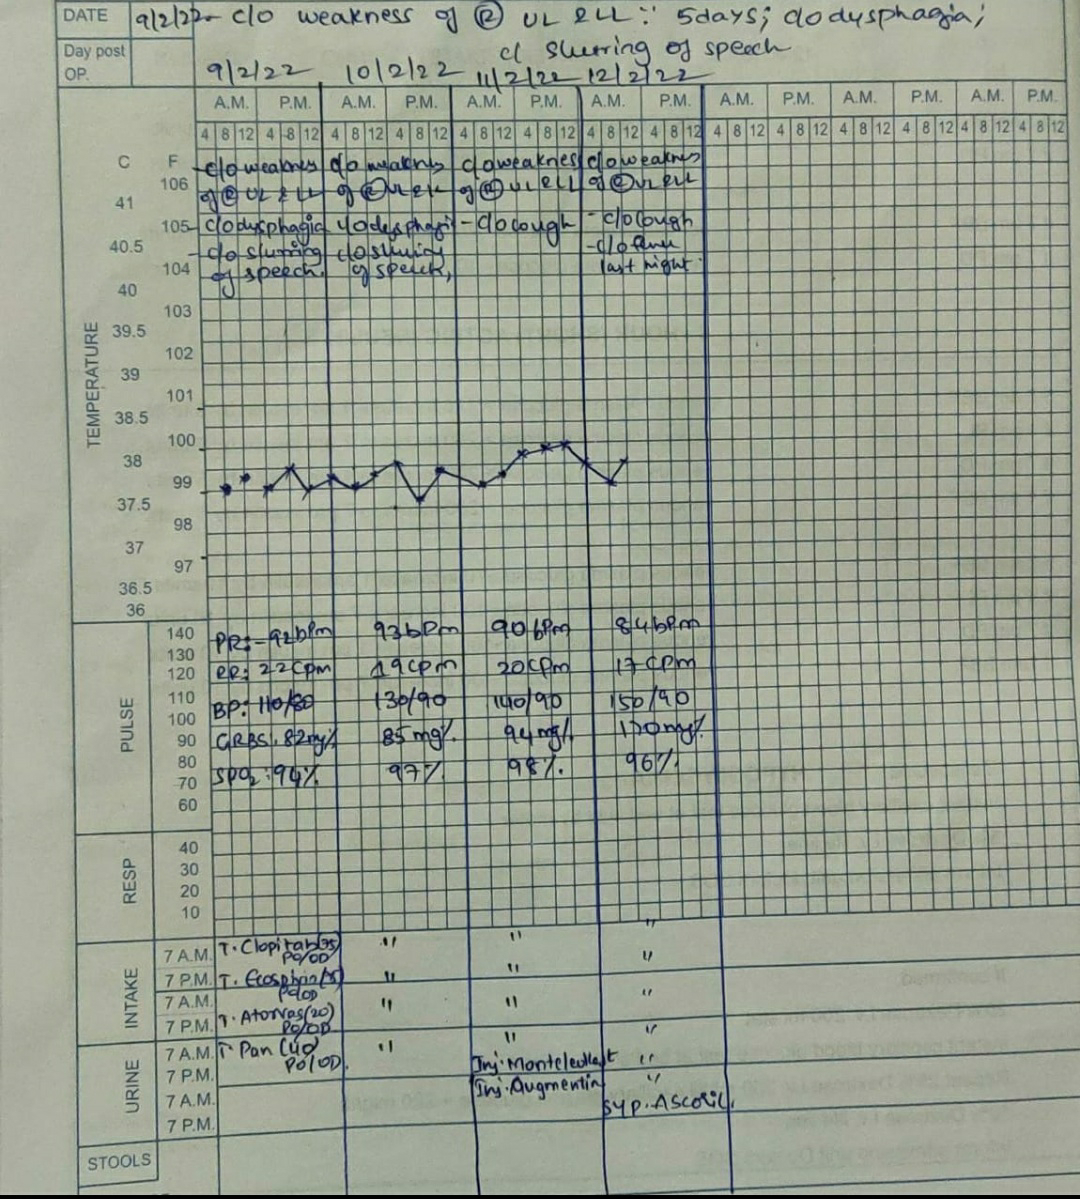
65Y MALE WITH C/O WEAKNESS OF RIGHT UL&LL

CBBLE UDHC SIMILAR CASES
THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HER /GUARDIAN'S SIGNED INFORMED CONSENT .HERE WE DISCUSS OUR INDIVIDUAL PATIENT'S PROBLEMS THROUGH SERIES OF INPUTS FROM AVAILABLE GLOBAL ONLINE COMMUNITY OF EXPERTS WITH AN AIM TO SOLVE THOSE CLINICAL PROBLEMS WITH COLLECTIVE CURRENT BEST EVIDENCE BASED INPUT 

A 65Y MALE WHO IS A DAILY WAGE LABOURER (SHEPHERD SINCE 10YRS) , CAME WITH COMPLAINTS OF WEAKNESS OF RIGHT UPPER LIMB AND LOWER LIMB SINCE 5 DAYS.

HOPI: 
PATIENT WAS APPARENTLY ASYMPTOMATIC 7YRS BACK.
 PATIENT HAD DINNER AROUND 8PM AND WENT TO SLEEP AROUND 2PM,HE WENT TO URINE AND SUDDENLY FELL IN BATHROOM, DIAGNOSED WITH RIGHT SIDED CVA AND ADVISED MEDICATION AND DISCHARGED.
IT TOOK AROUND 2-3 MONTHS TO WALK.NO SLURRING OF SPEECH AT THAT TIME,NO LOC.USED MEDICATION FOR 1YR AND STOPPED MEDICATION ON HIS OWN. RECOVERED APPROXIMATELY 75-80% (IN THEIR ATTENDERS LANGUAGE).
DIAGNOSED WITH HTN DURING ROUTINE CHECKUP AND STARTED ON ANTIHYPERTENSIVES BUT LATER STOPPED (AFTER 1 YR)
ONE WEEK BACK ,PT C/O UNABLE TO WAKEUP EARLY MORNING AFTER PASSING URINE.
C/O SLURRING OF SPEECH + , ABLE TO FEEL BLADDER FULL SENSATION.
C/O DYSPHAGIA +
C/O COUGH SINCE 3 DAYS.
NO C/O INVOLUNTARY DEFECATION 
NO C/O CHEST PAIN, SOB, PALPITATIONS.

PAST H/O : 
K/C/O HTN SINCE 1 YEAR WAS ON MEDICATION BUT STOPPED LATER
NOT A KNOWN CASE OF DM, BA, TB, CAD.

PERSONAL HISTORY:
DIET - MIXED,
APPETITE -NORMAL ,
BOWEL MOVEMENT - REGULAR , PASSED STOOLS 3 DAYS BACK
BLADDER MOVEMENTS - ABNORMAL
HABIT OF ALCOHOL CONSUMPTION (OCCASIONAL)
NO OTHER ADDICTIONS
NO KNOWN DRUG ALLERGIES

FAMILY HISTORY: NOT SIGNIFICANT

ON EXAMINATION 
PATIENT IS CONSCIOUS, COHERENT,COOPERATIVE
NO SIGNS OF PALLOR ,ICTERUS, CLUBBING, CYANOSIS, LYMPHADENOPATHY, PEDAL EDEMA.
VITALS: 
TEMP: 98.6°F
PR: 100 BPM
BP:110/80 MMHG
SPO2: 94% ON RA
GRBS: 83mg%

SYSTEMIC EXAMINATION: 
CARDIOVASCULAR SYSTEM : S1 AND S2 HEARD , NO MURMURS HEARD
RESPIRATORY SYSTEM : BILATERAL AIR ENTRY PRESENT ,NORMAL VESICULAR BREATH SOUNDS HEARD
PER ABDOMEN: 
SHAPE OF THE ABDOMEN : OBESE 
SOFT, NONTENDER, NO ORGANOMEGALY 
CNS:
 PATIENT IS CONSCIOUS WITH SLURRED SPEECH 
 NO NECK STIFFNESS ,
                           - RIGHT            LEFT

1) TONE UL NORMAL             NORMAL                                         LL NORMAL             NORMAL

2) POWER UL 4/5                  4/5
                      LL 3/5                  4/5

3) HANDGRIP 100%

4) REFLEXES  
       a) BICEPS    3+.                    2+
       b) TRICEPS 3+.                    2+ 
       c) SUPINATOR 3+               2+
       d) KNEE       2+.                     1+
       e) ANKLE       -                       -
       f) PLANTAR extensor          flexor

INVESTIGATIONS:

HEMOGRAM: 
HB: 15.4
TLC: 8,700
N/L/E/M/B: 78/12/02/08/00
PCV: 43.7
MCV: 37.8
MCH: 30.9
MCHC:35.2
RBC:4.98
PT:2.18
RDW-CV :13
RDW-SD: 42.5
PS: NC/NC

RFT:
BLOOD UREA : 22 MG/DL
SERUM CREATININE: 1.1
SERUM ELECTROLYTES:
Na+ : 135
K+: 4.1
Cl-: 98

LFT
TB: 2.11
DB: 0.94
SGOT:41
SGOT:26
ALP: 98
TP:7.4
ALBUMIN:3.83
A/G: 1.07

SEROLOGY: NEGATIVE
HBA1C : 6.5%
PLBS: 108mg/dl

SER.LIPID PROFILE: 
Total cholesterol: 196mg/dl
Triglycerides: 157mg/dl
HDL: 1.03
LDL:94
VLDL:31

TFT(10/2/22):
T3:1.03
T4;14.97
TSH:1.45


ECG: 
CXR
Repeat CXR(11/2/22):
2D ECHO: https://youtu.be/qDuJHzFoJAw
TRIVIAL TR+ / MR + / MILD ARD
GOOD RV& LV SYSTOLIC FUNCTION + 
NO RVMA , MIXED LVH + ,NO PAH
MINIMAL PE+ ; DIASTOLIC DYSFUNCTION + 

CT BRAIN: (DONE OUTSIDE ON 5/2/22)
IMP: 
ILL DEFINED PATCHY HYPODENSITY IN LEFT BODY OF CAUDATE NUCLEUS AND LEFT CORONA RADIATA-? SUBACUTE TO CHRONIC INFARCT
CHRONIC LACUNAR INFARCTS IN BILATERAL CAPUSLOGANGLIONIC REGIONS AND BILATERAL CORONA RADIATA
DIFFUSE CEREBRAL ATROPHY
CHRONIC SMALL VESSEL ISCHEMIC CHANGES

USG ABD AND PELVIS:(10/2/22)
NO SONOLOGICAL ABNORMALITY DETECTED

COLOR DOPPLER(10/2/22)
MRI BRAIN(11/2/22):
-Acute infarcts in right caudate nucleus,putamen, internal capsule and adjacent corona radiata.
-Mild diffuse cerebral and cerebellar atrophy with small vessel ischaemic changes.

TREATMENT PLAN
T.CLOPITAB   75MG PO/OD
T.ECOSPIRIN 75MG PO/OD
T.ATORVAS     20MG PO/OD
T.PAN 40 MG PO/OD


                           SOAP NOTES

DAY 1:
AMC BED 2
S: Patient c/o cough

O: 
Pt c/c/c 
Temp:- 98.6°F
PR 86
SPO2 97%
GRBS 87mg%
BP 130/80mmhg
CVS: S1S2 HEARD
RS: BAE+
P/A: SOFT,NONTENDER
CNS                  RIGHT.                 LEFT     
POWER      
     UL.               3/5                    3/5
     LL                4/5                    4/5
TONE     
       UL.           . increased       normal
        LL.             increased      normal
4) REFLEXES  
  a) BICEPS   3+                    2+
  b) TRICEPS 3+                   2+ 
  c) SUPINATOR 3+             2+
  d) KNEE       3+                   2+
  e) ANKLE.         -                  -
  f) PLANTAR extensor   flexor

A: Subacute R sided CVA with Subacute infarct in L CAUDATE nucleus & L corona RADIATA with hypertension

P : 
T. Clopitab 75mg 
T. Ecospirin 75mg
T. Atorvas 20mg 
T. Pan 40 mg  
T. Monteleukast
Syp.Ascoril
Planned for 2decho and Color Doppler

DAY 2:
S: Patient c/o cough

O: 
Pt c/c/c 
Temp:-98.8°F
PR 92
SPO2 98%
GRBS 94mg%
BP 140/90mmhg

CVS: S1S2 HEARD
RS: BAE+
P/A: SOFT,NONTENDER
CNS               RIGHT         LEFT     
 POWER      
     UL              3/5                3/5
     LL              4/5                 4/5
TONE     
     UL.             increased       normal
      LL.             increased.     normal
REFLEXES  
  a) BICEPS.       3+                   2+
  b) TRICEPS    3+                    2+ 
  c) SUPINATOR 3+                 2+
  d) KNEE.           3+                  2+
  e) ANKLE          -                     -
  f) PLANTAR extensor          flexor

A: Subacute R sided CVA with Subacute infarct in L caudate nucleus & L corona radiata with hypertension

P : 
T. Clopitab 75mg 
T. Ecospirin 75mg
T. Atorvas 20mg 
T. Pan 40 mg 
T. Monteleukast
Inj.optineuron 
Inj.Augmentin
Syp.Ascoril
Planned for MRI BRAIN, repeat cxr

DAY 3:-
S:Patient c/o cough, one fever spike yesterday night

O: 
Pt c/c/c 
Temp:97°F
PR 85bpm
SPO2 96%
GRBS 170mg%
BP 150/90mmhg

CVS: S1S2 HEARD
RS: BAE+
P/A: SOFT,NONTENDER
CNS               RIGHT          LEFT     
 POWER      
     UL.              3/5                 3/5
     LL                4/5                 4/5
TONE     
     UL.         increased       normal
      LL.        increased        normal
REFLEXES  
  a) BICEPS.      . 3+             2+
  b) TRICEPS      3+             2+ 
  c) SUPINATOR 3+            2+
  d) KNEE.             3+          2+
  e) ANKLE           -              -
  f) PLANTAR extensor    flexor

A: Subacute R sided CVA with Subacute infarct in L caudate nucleus & L corona radiata with hypertension

P : 
T. Clopitab 75mg po od 
T. Ecospirin 75mg po od
T. Atorvas 20mg po od
T. Pan 40 mg po od
T. Monteleukast po od
T.Amlong 5mg po od
T.Pcm 500mg po qid
Inj.optineuron 1ampin100ml/ns/od
Inj.Augmentin 1.2mg/iv/tid
Syp.Ascoril 5ml po tid 
Monitor Temp/Bp/grbs 4th hrly
Planned for Fundoscopy

75Y/F WITH C/O SOB AND FEVER

CBBLE UDHC SIMILAR CASES  THIS IS AN ONLINE E LOG BOOK TO DISCUSS OUR PATIENT'S DE - IDENTIFIED HEALTH DATA SHARED AFTER TAKING HIS / HE...